Treatment GuideJust DiagnosedSex & DatingAfrican AmericanStigmaAsk the HIV DocPrEP En EspañolNewsVoicesPrint IssueVideoOut 100
CONTACTCAREER OPPORTUNITIESADVERTISE WITH USPRIVACY POLICYPRIVACY PREFERENCESTERMS OF USELEGAL NOTICE
© 2026 Pride Publishing Inc.
All Rights reserved
All Rights reserved

By continuing to use our site, you agree to our Privacy Policy and Terms of Use.

The ability to actually measure the amount of virus in blood was a huge leap forward in the treatment of HIV. In the early 1990s a technique called polymerase chain reaction was developed as a method to look for organisms by identifying their genetic makeup. Before PCR, the usual way for a clinician to know if a virus was present in blood was to look for antibodies to the virus, but finding antibodies gives only indirect evidence of viral exposure, not true presence of the virus. The advantage with PCR is that we had a tool that said whether the virus was still present. However, it did not tell us how much virus was there. So the only way we could monitor patients' response to antiretrovirals was to watch T-cell counts. Once T-cell counts started to drop we knew we had to try something different. It was a little like closing the barn door once the horse was out. In 1995, though, two milestones were achieved at the same time. First, quantitative PCR was developed, allowing us to count the number of virus copies in a milliliter of blood. Second, we learned that if you combined a pair of the nucleoside analogs available at that time, such as AZT and 3TC, along with a new class of antivirals called protease inhibitors, you could see the viral load fall steadily to undetectable levels and stay there. I clearly remember hearing this presented for the first time at the retroviral conference in Washington, D.C., in early 1996. A graph was shown of the counts of one patient in an early protease inhibitor trial who initially had viral loads done every six hours starting with the first dose. By the second week the viral load started to fall precipitously to undetectability, which was maintained through 24 weeks when this was reported. The audience was amazed and elated. Today, almost all viral loads are measured by one of two different methods: PCR or branched chain DNA. They give roughly the same numbers, with bDNA generally being a little lower. Although the science is different between the two, they both involve a step of amplification or multiplication of the virus. It is this step that creates wide swings in viral loads. If a small variation in the virus count occurs early in the multiplication process, then this variation is multiplied along with the virus. This is the reason that viral loads must change by at least threefold to fivefold to be significant. So if your true viral load is 600, a dip to 420 or a jump to 950 may look meaningful, but they are really all in the same range. Similarly, if your viral load is 120, measurements may bounce between 80 and 250. As I said in this column on T-cell counts in the August issue, trends over time are the best way to know if the viral load is moving up or down. Finally, routine viral load tests generally have a range of 400 to 750,000. Ultrasensitive viral loads can test down to a 25-to-75 viral-copy range, depending on the lab. Levels below these cutoffs are called undetectable. In this range 'blips' can occur. A blip is defined as a viral load that rises from undetectable to measurable and then falls back to undetectable. Most clinicians do not feel that an occasional blip means anything. It may be caused by what the lab folks call 'background noise''that is, when you are measuring such a low level of virus it is sometimes difficult to distinguish what is virus and what is just artifact. During this tutorial on viral loads I hope you appreciated the bit of HIV history. As you see, the science of HIV research is more than just drug development. It has created amazing new tools essential for advancing the fight against HIV. And now it is also immensely helpful in other areas of viral research, such as tracking down severe acute respiratory syndrome or monitoring treatments for hepatitis. Who knows what tomorrow might bring? Bowers is board-certified in family practice and is a senior partner with Pacific Oaks Medical Group, one of the nation's largest practices devoted to HIV care.


From our Sponsors
Most Popular

The road to U=U: How science has been liberating HIV+ people for a decade
July 01 2026 12:05 PM

Newly diagnosed with HIV? Advocates share their best advice for seeking treatment
April 29 2026 3:32 PM

How to find an HIV-competent healthcare provider, according to advocates
May 19 2026 4:55 PM
Plus: Featured Video
Latest Stories
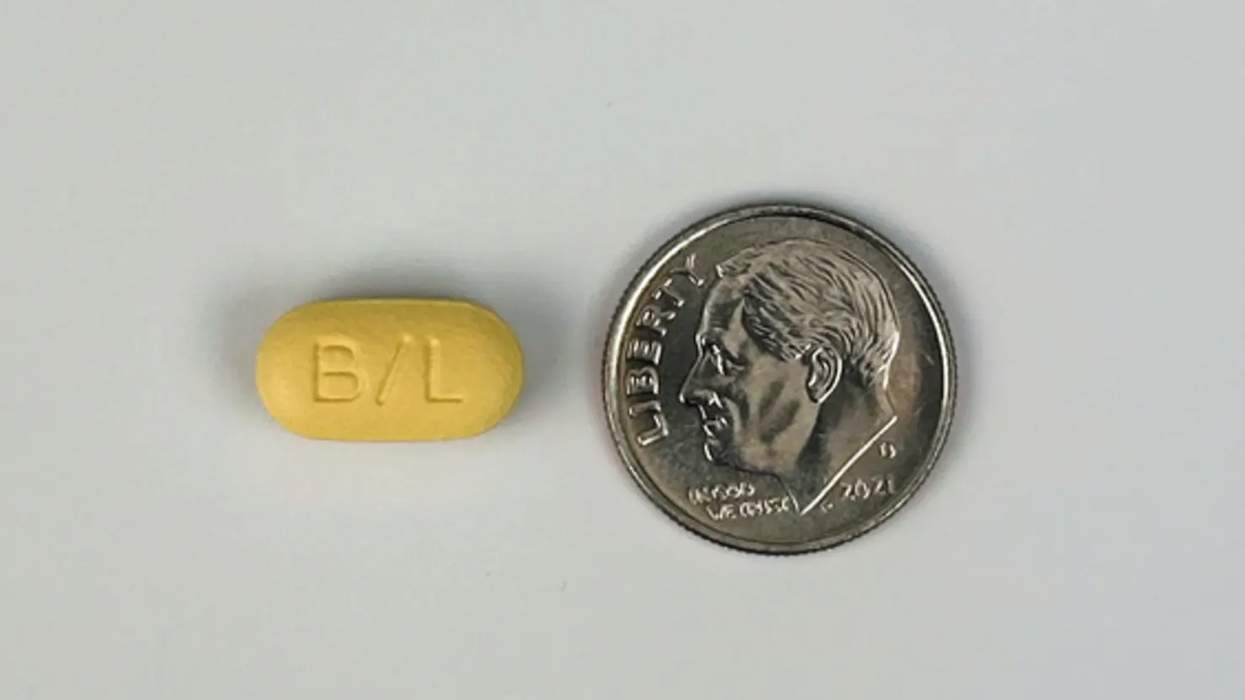
A New Once-Daily Pill to Treat HIV Just Got the FDA’s Green Light
August 31 2026 2:31 PM

Why affirming faith communities belong in the fight to end HIV
August 30 2026 8:00 AM

Navigating a new HIV diagnosis? Advocates say community is key
August 25 2026 3:33 PM

Gay Wine Weekend toasts 15 years of raising funds for HIV
August 25 2026 11:00 AM



A new HIV diagnosis doesn't have to be nerve-wracking. Advocates share their advice
July 30 2026 12:01 PM
Zero HIV Stigma Day: The epidemic we still choose to ignore
July 21 2026 7:00 AM

National HIV Prevention Day: Awareness is my superpower
July 17 2026 8:00 AM

Federal court clarifies that people with HIV can join the military again
June 03 2026 5:36 PM

Can a single infusion of immune cells suppress HIV for years?
May 11 2026 11:39 AM


National HIV advocacy group's CEO rejects claims of crisis
April 21 2026 5:14 PM

Beyond awareness: How youth leadership is reshaping the HIV response
April 10 2026 9:12 AM

Saving public health? AIDS United's new CEO has a plan
March 23 2026 9:48 AM
Struggling with daily HIV meds? Monthly shots may be the answer
March 20 2026 7:12 AM

Trending stories














Recommended Stories for You























